 blog
Can Neck Pain Be Treated Without Surgery?
Last Updated: November 3, 2026
Quick Summary
Yes, most people with neck pain do not need surgery, and neck pain treatment usually starts with conservative care such as supervised exercise and manual therapy. A clinical guideline review led by P. Kjaer (2017) recommended supervised exercise and manual therapy, including combinations of the two, as the backbone of nonsurgical care.
- Apply ice for the first 48 hours, then switch to heat therapy to relax muscle spasm.
- Epidural steroid injections have the strongest evidence among cervical injections, mainly for radicular symptoms.
- Radiofrequency ablation is reserved for chronic, confirmed facet-mediated pain after two successful diagnostic blocks.
- Seek prompt evaluation for progressive weakness, gait change, or bowel or bladder dysfunction.
- If a plan has not helped in six to eight weeks, re-examine the diagnosis rather than repeating treatment.
Table of Contents
- Nonsurgical Neck Pain Treatment Options Compared
- Chiropractic Care for Neck Pain: What the Evidence Shows
- Neck Pain Relief at Home: Cold and Medications
- Injections and Interventional Care
- Chronic Neck Pain Treatment: Matching Care to Your Diagnosis
- Schedule a Consultation at Minnesota Chiropractic and Rehabilitation
- Frequently Asked Questions
Nonsurgical Neck Pain Treatment Options Compared
Most people with neck pain do not need surgery. Most people with neck pain do not need surgery, and the options are wider than many patients expect.
A clinical guideline review led by P. Kjaer (2017) examined 21 non-surgical interventions for recent-onset neck pain and recommended supervised exercise and manual therapy, including combinations of the two, the backbone of conservative care (pubmed.ncbi.nlm.nih.gov).
Here is how the main options stack up:
Treatment | Best For | Typical Role |
|---|---|---|
Stretching and exercise | Most neck pain, muscle strain | First-line care |
Cold, OTC medication | Mild to moderate pain | Symptom relief |
Spinal Decompression | Disc-related pain | Non-Surgical Disc Care |
Chiropractic Care | Joint related pain | Corrective Care |
Injections | Nerve compression, facet pain | Targeted Care |
The key insight most guides miss: these options are not interchangeable. Each fits a different cause. For a closer look at the clinic's approach, see neck pain care in Plymouth, MN.
Chiropractic Care for Neck Pain: What the Evidence Shows
Chiropractic Care is the best-supported nonsurgical treatment for neck pain. It combines correction of the spinal alignment with strengthening, flexibility, and posture work to reduce strain on the cervical spine.
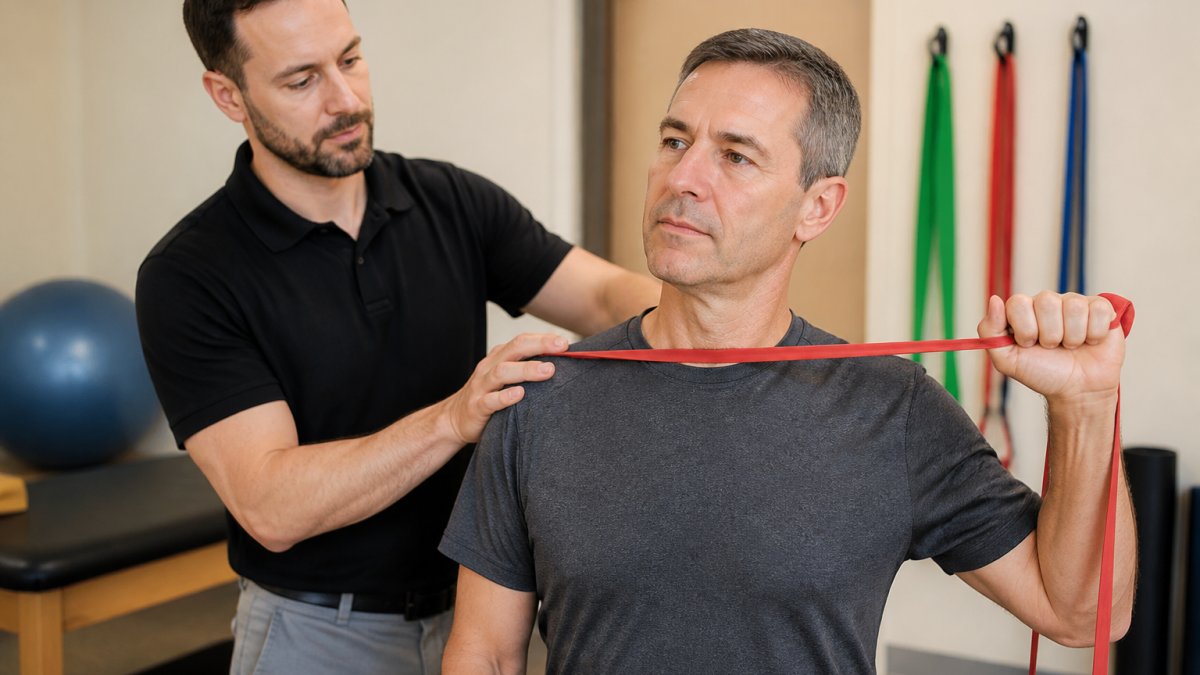
Guiding a patient through neck pain treatment exercises in a bright clinic setting
Guiding a patient through neck pain treatment exercises in a bright clinic setting
The evidence is strong. Hurwitz (2008) found that therapies combining manual therapy and exercise were effective for for neck pain, as documented in the Treatment of Neck Pain evidence synthesis.
A typical program includes:
- Supervised therapeutic exercise
- Manual therapy and joint mobilization
- Strengthening for neck and shoulder muscles
Structured programs, like our treatment programs, are available for patients seeking active rehabilitation.
Neck Pain Relief at Home: Cold and Medications
Home care handles mild to moderate pain well. The Mayo Clinic's guidance on neck pain notes that nonprescription pain medicine plus ice are often enough to ease symptoms.
Simple steps that help:
- Apply ice for the first 72 hours to reduce inflammation
- Moist heat can be applied afterwards to help relax muscles.
- Use over-the-counter pain relievers as directed
Watch out: do not stay in one position for hours hoping pain will pass. Gentle movement protects mobility.
Injections and Interventional Care
No treatment cures neck pain overnight. Injections are sometimes used to ease a flare in order to utilize more conservative options. They deliver medication directly to the structure generating pain, so the diagnosis has to come first, an injection into the wrong tissue does nothing and carries its own risk.
The main interventional options
- Epidural steroid injection. Deposits corticosteroid near the nerve root or in the epidural space to reduce inflammation from a herniated disc or foraminal narrowing. Best suited to radicular pain that travels into the arm. Relief is often temporary, weeks to a few months, and is used to create a window for therapy rather than as a stand-alone cure.
- Facet joint injection. A corticosteroid and local anesthetic mix delivered into or around a cervical facet joint. Used when pain is axial, worse with extension and rotation, and reproduced on exam. A positive response to a diagnostic medial branch block is what justifies moving to radiofrequency ablation.
- Trigger point injection. Local anesthetic, sometimes with steroid, into a taut band of muscle. Reasonable for myofascial pain with palpable knots; evidence is modest and effect is usually short-lived, so it works best paired with exercise.
What the evidence actually supports
Epidural steroid injections have the strongest evidence among cervical injections, particularly for radicular symptoms, though benefit over placebo narrows beyond the short term. Facet interventions depend heavily on correct patient selection, the diagnostic block matters more than the injection itself. Trigger point injections have weaker, inconsistent evidence, and PRP for cervical disc degeneration remains under study.
Risks and who should not get them
- Infection at the injection site, uncommon but serious in the epidural space.
- Bleeding and bruising, higher risk with blood thinners.
- Nerve irritation or transient numbness from needle placement.
Contraindications include active infection, uncontrolled bleeding disorders, allergy to the injected agent, and, for steroid injections, poorly controlled diabetes that warrants a conversation with the prescribing physician first. Pregnancy and anticoagulation require individualized planning.
Where injections sit in the sequence
Injections are not first-line. The usual path is conservative care first, activity modification, physical therapy, and nonprescription medication, and an injection when pain is severe enough to block participation in therapy, or when radicular symptoms persist despite several weeks of conservative treatment. Readers can explore acupuncture as an interventional option for faster relief.
Watch out: a provider who offers an injection before examining you, reviewing imaging, or explaining what happens if it fails is skipping the step that determines whether the procedure can work at all.
Chronic Neck Pain Treatment: Matching Care to Your Diagnosis
Chronic neck pain, pain lasting beyond roughly three months, rarely has a single cause, and the treatment that works depends on which structure is generating the pain. The 2017 guideline led by P. Kjaer did not endorse every non-surgical option equally: evidence quality varies widely by treatment and diagnosis. Because a herniated disc is only one possible source of neck pain, non-surgical options for pain should be considered in light of the specific structure involved and the evidence for each approach.
Match the treatment to the likely cause
- Muscle strain or myofascial pain. The most common pattern: axial pain, worse with sustained posture, often with palpable tight bands. First-line care is supervised exercise, manual therapy, and ergonomic correction. Evidence is strongest here, and most patients improve.
- Cervical radiculopathy (nerve compression). Pain radiates into the arm, often with numbness, tingling, or weakness in a specific nerve distribution. Imaging may show a herniated disc or foraminal narrowing. Conservative care, Non-surgical spinal decompression, chiropractic care, and a short course of medication, resolves most cases over weeks to a few months. Epidural steroid injection is reasonable when pain blocks therapy or persists. Surgery is reserved for progressive weakness or refractory symptoms.
- Facet joint pain. Axial pain, worse with extension and rotation, often with referred pain to the shoulder or head. Diagnosed with a medial branch block. Treatment escalates from chiropractic care to facet injection to radiofrequency ablation when blocks confirm the joint as the source.
A practical escalation pathway
- Weeks 0-2: activity modification, relative rest without prolonged immobilization, ice, nonprescription anti-inflammatories as directed, and gentle range-of-motion work along with chiropractic care to relieve joint pressure in the neck.
- Weeks 2-6: strengthening and manual therapy, chiropractic care. Consider non-surgical spinal decompression.
- Weeks 6-12: if pain persists or blocks function, reassess the diagnosis. Consider imaging if not already done, and a targeted injection for radicular or facet-mediated pain.
Watch out: repeating a treatment that produced no benefit after a fair trial is one of the most common ways patients lose months. If a plan has not moved the needle in six to eight weeks, the diagnosis, not just the dose, should be re-examined.
Red flags that change the plan
Some symptoms take neck pain out of the conservative-care category entirely. Seek prompt or emergency evaluation for new or progressive weakness in the arms or hands, loss of coordination or gait change, bowel or bladder dysfunction, severe pain after trauma, fever with neck stiffness, unexplained weight loss, or a history of cancer.
For disc-related pain, spinal decompression therapy is the most effective non-surgical option.
Schedule a Consultation at Minnesota Chiropractic and Rehabilitation
Choosing care starts with an honest look at your symptoms. Red flags like severe weakness, loss of coordination, or pain after trauma need prompt medical review.
For everyone else, conservative care is a reasonable first step. Our patient-centered approach includes non-invasive options such as chiropractic care, spinal decompression, shockwave therapy, and acupuncture.
Frequently Asked Questions
What are the most effective nonsurgical treatments for neck pain?
For mild to moderate pain, the Mayo Clinic notes that nonprescription pain relievers plus ice often ease symptoms. Other options include muscle relaxants, TENS, chiropractic care, massage, non-surgical spinal decompression, steroid or epidural injections, facet joint and trigger point injections, if nothing else has helped. The right neck pain treatment depends on your diagnosis and symptom pattern, so a clinical evaluation should come first.
Can neck pain go away without surgery?
Many cases do improve with conservative care. Some evidence syntheses have examined manual therapy and exercise for neck pain. The 2017 guideline recommends exercise and manual therapy for recent-onset nonspecific neck pain and cervical radiculopathy. That said, evidence is not uniform across all 21 interventions reviewed, so results vary by cause and by treatment. Red flags such as progressive weakness, loss of coordination, or bowel or bladder changes need urgent medical assessment rather than a wait-and-see approach.
When should I seek medical care for neck pain?
Seek care promptly if neck pain follows a fall or motor vehicle collision, or comes with severe headache, fever, numbness, progressive arm weakness, or difficulty walking. These can signal nerve compression or a more serious condition. For pain lasting more than a few weeks, or that keeps returning, a clinical evaluation helps identify the cause and guide chronic neck pain treatment. A provider can assess whether physical therapy for neck pain, injections, or another approach fits your situation.
What can I do at home to relieve neck pain and stiffness?
The Mayo Clinic lists nonprescription pain medicine and applying ice as typical first steps for mild to moderate neck pain. Gentle range-of-motion movement and attention to posture during desk or phone work can reduce strain, and short periods of rest may help during a flare. Avoid prolonged immobilization, which can weaken muscles. If home measures do not improve symptoms within a few weeks, or if pain radiates into the arm, ask a clinician about other nonsurgical options.
Neck pain rarely requires surgery, but it does require the right plan. If home care and therapy have not delivered lasting relief, we can help you find what fits. Get started with Minnesota Chiropractic and Rehabilitation and book your appointment to build a care plan around your diagnosis.